
































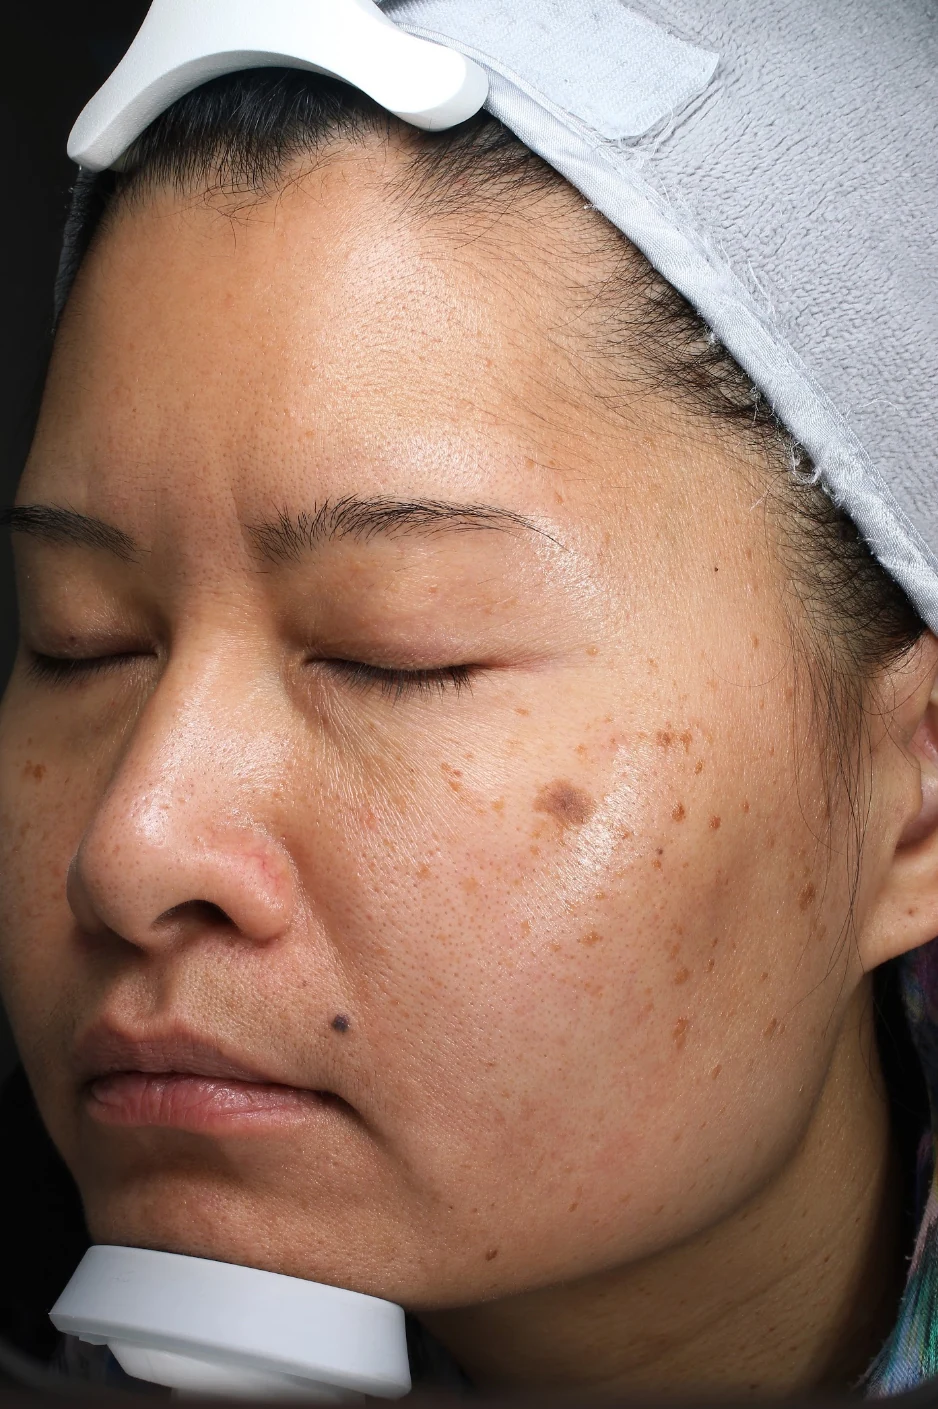

Retinol is Overrated? What a Cosmetic Doctor Actually Thinks About Retinol
A cosmetic doctor cuts through the hype to explain what retinol genuinely does, where it falls short, and why misuse is the real problem — not the ingredient itself.

Key Takeaways
- Retinol is one of the most thoroughly researched topical skincare ingredients in dermatology, with solid evidence for improving texture, fine lines, pigmentation, and acne.
- Persistent peeling and redness are signs of barrier damage caused by misuse, not indicators that the product is working harder or delivering faster results.
- Deep expression lines such as frown lines require injectable treatments like Botox or filler — no over-the-counter retinol cream can replicate that effect.
- Starting at a low concentration and increasing gradually is clinically safer and more effective than jumping straight to a high-strength formula.
- Retinol is a night-only ingredient that breaks down under UV exposure and must always be paired with a broad-spectrum sunscreen during the day to avoid worsening pigmentation.
Direct Answer
Retinol is a vitamin A derivative that, once absorbed, converts to retinoic acid in the skin and binds nuclear receptors to accelerate cell turnover, stimulate collagen and elastin production, and block the UV-activated enzymes that degrade collagen. Decades of peer-reviewed research support its use for smoothing surface texture, softening fine lines caused by sun damage, fading uneven pigmentation, and reducing acne. What is overrated is the marketing promise that retinol addresses every skin concern equally well: it does not erase deep expression lines, and the peeling many users chase is a sign of barrier damage, not accelerated results. At ID Cosmetic Clinic in Markham, Dr. Dan Xu, MD, CCFP, regularly sees patients who arrive either disappointed that retinol did not 'fix' their frown lines or with irritated, sensitised skin from starting at too high a concentration too quickly. Dr. Xu's clinical approach emphasises that retinol is a proven, valuable tool when used correctly — low concentration, gradual increase, night-only application, and consistent daytime sunscreen — but it works best as part of a broader, medically guided skincare plan rather than as a standalone solution to all ageing concerns.
Quick answer: Retinol is neither a miracle nor a scam. It is one of the best-studied skincare ingredients in the world, with strong evidence for smoothing texture, improving fine lines, fading pigment and treating acne. What’s overrated is the marketing promise that retinol “fixes everything.” It will not erase deep frown lines, and the peeling so many people chase is not proof it’s working — it’s usually a sign of misuse. Below, a cosmetic doctor separates what retinol genuinely does from the hype.
Medically reviewed by Dr. Dan Xu, M.D., CCFP — CPSO Licensed Physician and Founder & Medical Director of ID Cosmetic Clinic, Markham. Last updated June 2026.
Retinol may be the most over-promised ingredient on the skincare aisle. Patients walk into our Markham clinic convinced it will melt away every wrinkle, only to feel let down — or, just as often, with raw, peeling skin from using it wrong. The honest reality sits in between. Retinol has decades of solid clinical research behind it, but the “does-everything” image is a marketing creation, not a scientific one. So is retinol overrated? Let’s go myth by myth and look at what the evidence actually shows.
Retinol myths vs facts
| The myth | The truth |
|---|---|
| “Retinol is overrated and doesn’t really work” | It is one of the most evidence-backed ingredients in dermatology for texture, fine lines, pigment and acne. |
| “Retinol erases all wrinkles” | It softens fine, sun-related lines — but deep expression lines need Botox or filler, not a cream. |
| “Peeling and redness mean it’s working” | Mild renewal is fine; persistent peeling and stinging mean your barrier is damaged, not that you’re getting more results. |
| “Higher percentage = faster results” | Starting too strong causes irritation that sets you back. Low and slow wins. |
| “You can use retinol any time of day” | Retinol degrades in UV light — it’s a night-only product, always paired with daytime sunscreen. |
| “Retinol and tretinoin are the same” | Tretinoin is the prescription active form; retinol is a weaker over-the-counter precursor that must convert in the skin. |
| “Layer it with your acids for a bigger punch” | Stacking strong acids with retinol the same night multiplies irritation and barrier damage. |
Myth 1: “Retinol is overrated and doesn’t really work”
The truth: This is the myth that gets retinol the most unfair reputation. Retinol — and its prescription cousin tretinoin — is among the most thoroughly researched topical ingredients in all of dermatology. Once it converts to retinoic acid in the skin, it binds nuclear retinoic-acid receptors and changes gene expression: it speeds up the turnover of surface skin cells, stimulates fibroblasts to build new collagen and elastin, and inhibits the enzymes (matrix metalloproteinases) that UV exposure activates to break collagen down. In plain terms, the evidence genuinely supports smoother texture, softer fine lines, more even tone and fewer breakouts. Retinol isn’t overrated — the expectations placed on it often are.
Myth 2: “Retinol will erase all my wrinkles”
The truth: Here’s where the marketing overreaches. Retinol has clear, well-documented benefits for fine, superficial lines caused by sun damage and early collagen loss. But it has very limited effect on deep, dynamic expression lines — the frown lines between the brows, the crow’s feet around the eyes — because those are driven by repeated muscle movement, not surface skin quality. No cream relaxes a muscle. Those lines are the domain of Botox and, for etched-in static folds, dermal filler. Expecting retinol to “erase” them sets you up for disappointment and is the single biggest reason people wrongly conclude it doesn’t work.
Myth 3: “Peeling and redness mean it’s working”
The truth: This is one of the most persistent and most damaging retinol myths. The flaking, redness and dryness of the early “retinol reaction” get reframed online as proof the product is doing its job. A modest acceleration in skin-cell turnover is part of how retinol works — but ongoing peeling, stinging, burning and irritation are signs your skin barrier is being damaged, not that you’re getting superior results. A compromised barrier often forces you to stop entirely and repair, which delays the real benefits. Visible, healthy results come from consistent, tolerable use over months — not from how much your skin flakes.
Myth 4: “A higher percentage works faster”
The truth: Strength is not the same as success. First-time users should begin with a low concentration (around 0.025–0.05%) and give the skin roughly four to eight weeks to adapt before stepping up. Jumping straight to a 1% product is the classic mistake — it commonly triggers a severe reaction with peeling, burning and inflammation, damages the barrier, and ends with the product banished to the back of a drawer. The people who get the best long-term results are usually the ones who started low, went slow, and stayed consistent. With retinol, restraint outperforms aggression.
Myth 5: “You can use retinol any time of day”
The truth: Retinol is photo-unstable — it degrades quickly in UV light. Used in the morning, much of its potency is lost, and it can increase photosensitivity and your risk of sunburn. Retinol belongs strictly to your nighttime routine, and daytime sunscreen is non-negotiable while you use it. Skipping sun protection doesn’t just blunt your results; it actively works against the collagen retinol is trying to build, because UV exposure drives the very breakdown you’re treating.
Myth 6: “Retinol and tretinoin are the same thing”
The truth: They’re related, but not identical — and the difference matters. Retinol is an over-the-counter precursor that must convert through two steps in the skin to become retinoic acid, the active form. That conversion loses potency along the way, so retinol is gentler but weaker. Retinaldehyde sits in the middle: it needs only one conversion step, so it’s stronger than retinol and milder than the prescription form. Tretinoin (retinoic acid) is the direct active form — no conversion needed, the strongest effect and the deepest clinical evidence, but also the most irritating, and in Canada it requires a physician’s prescription. If over-the-counter retinol hasn’t delivered after a few months of correct use, stepping up to a prescription retinoid under medical supervision is a reasonable next move.
Myth 7: “Layer it with your acids for a bigger punch”
The truth: Stacking retinol with high-strength AHA or BHA exfoliating acids in the same routine doesn’t double your results — it compounds the irritation and significantly raises your risk of barrier damage. These actives are best separated: alternate acids and retinol on different nights, or have a clinician design a schedule suited to your skin. “More actives at once” is one of the fastest ways to end up with red, reactive skin and no benefit to show for it.
Who should be cautious with retinol?
Retinol suits most people, but not everyone, and not at every moment. You should avoid or postpone retinol if you are pregnant or breastfeeding (retinoids are generally avoided in pregnancy — speak to your doctor), if you have very sensitive or reactive skin, active eczema, rosacea or a compromised skin barrier, or an active skin infection or open irritation where you’d apply it. If you use other prescription topicals or are about to have a procedure such as a chemical peel, laser or microneedling, tell your clinician — retinol is usually paused around those treatments. People primarily with Asian skin, which our clinic largely serves, can be more prone to post-inflammatory pigmentation when the barrier is over-stressed, which makes the “low and slow” approach especially important. This article is general information, not medical advice; a proper consultation tailors any plan to your skin.
The real takeaway
Retinol is not overrated — but the marketing around it is. It is a genuinely powerful, evidence-based ingredient for texture, fine lines, tone and acne, and it deserves its place in many routines. What it is not is a cure-all. It won’t erase deep expression lines, and the peeling people chase as a badge of honour is usually a sign they’re using it wrong. Start low, use it at night, protect with sunscreen, and don’t pile it on top of acids. Used patiently and correctly, retinol quietly earns its reputation. Used aggressively, it earns its myths.
Frequently asked questions
Is retinol overrated?
No — but the expectations are. Retinol has strong evidence for improving texture, fine lines, tone and acne. What’s overrated is the marketing idea that it fixes everything, including deep wrinkles it can’t reach.
Does retinol really get rid of wrinkles?
It softens fine, sun-related lines and improves overall texture, but it does not erase deep expression lines like frown lines or crow’s feet. Those are caused by muscle movement and need Botox or filler, not a cream.
Does peeling mean my retinol is working?
No. Mild renewal is normal, but persistent peeling, stinging and redness mean your skin barrier is being irritated, not that you’re getting better results. Healthy results come from consistent, tolerable use over months.
What percentage of retinol should I start with?
Begin low, around 0.025–0.05%, and give your skin four to eight weeks to adjust before increasing. Starting too strong usually causes irritation that sets you back rather than speeding things up.
Can I use retinol in the morning?
It’s best at night. Retinol breaks down in UV light, so daytime use reduces its potency and can increase sun sensitivity. Always pair retinol with a daytime sunscreen.
What’s the difference between retinol and tretinoin?
Tretinoin is the prescription, direct active form (retinoic acid) — stronger and better studied but more irritating. Retinol is a gentler over-the-counter precursor that must convert in the skin, making it weaker but more tolerable.
Can I use retinol with my exfoliating acids?
Not in the same routine. Stacking retinol with strong AHA or BHA acids multiplies irritation. Alternate them on different nights, or have a clinician design a schedule for your skin.
How long until I see results from retinol?
Texture and breakouts often improve within several weeks, but fine lines and tone typically take three to six months of consistent use. Retinol rewards patience, not intensity.
Should I switch from retinol to a prescription retinoid?
If over-the-counter retinol hasn’t delivered after a few months of correct use, upgrading to a prescription retinoid under a physician’s guidance is a reasonable next step — best decided in a consultation.
Related at ID Cosmetic Clinic
- Treatment: Medical-Grade Skincare & Retinoids
- Treatment: Chemical Peels
- Concern: Fine Lines & Wrinkles
- Concern: Acne & Breakouts
- Read next: The Truth About Botox: 7 Myths Debunked
Not sure if retinol is right for your skin? Book a consultation at ID Cosmetic Clinic in Markham — Dr. Dan Xu will give you an honest, conservative skincare plan built around what your skin actually needs.
📍 30 Gibson Dr, Units 113-117, Markham, ON L3R 2S3 · 📞 905-477-2225 · ✉️ [email protected] · 🕒 Mon–Sun 10:00–18:00
Frequently Asked Questions
Frequently Asked Questions
Is retinol overrated?
Does retinol really get rid of wrinkles?
Does peeling mean my retinol is working?
What percentage of retinol should I start with?
Can I use retinol in the morning?
What is the difference between retinol and tretinoin?
Can I use retinol with my exfoliating acids?
How long until I see results from retinol?
Should I switch from retinol to a prescription retinoid?
Next Step
Ready to Take the First Step?
Laxity, wrinkles and facial sagging have different root causes — one physician-led consultation identifies the true problem layer before deciding which plan fits you best.
